The Evolving Paradigm of Early-Stage NPC Treatment
Nasopharyngeal carcinoma, originating from the mucosal lining of the nasopharynx, is the most common epithelial carcinoma of the head and neck. While globally less common than some other cancers, its incidence is notably higher in specific geographic regions, particularly Southeast Asia and Southern China, where it is strongly associated with the Epstein-Barr virus (EBV) and genetic predisposition. For decades, the standard of care for early-stage NPC, even with localized lesions, has leaned heavily towards radiotherapy. This approach was largely dictated by the complex anatomy of the nasopharynx, which makes surgical access for complete tumor removal extremely challenging, and the significant risk of lymphatic spread, even in the nascent stages of the disease.
However, the past decade has witnessed a paradigm shift driven by two key factors: improved diagnostic capabilities and a growing demand for less morbid treatment options. Enhanced health education and widespread implementation of early cancer screening programs have resulted in a significant uptick in the detection of NPC at its earliest stages. Studies indicate that a substantial proportion of NPC patients, ranging from 47.1% to 51.1%, are diagnosed with stage I disease, characterized by tumors confined within the nasopharyngeal cavity. This burgeoning cohort of early-stage patients has amplified the imperative for minimally invasive treatment modalities that can achieve curative outcomes without the long-term side effects often associated with radiotherapy, such as xerostomia (dry mouth), hearing loss, and potential secondary malignancies.
Prior research has already laid the groundwork for endoscopic interventions in NPC. Endoscopic nasopharyngectomy (ENPG) has demonstrated feasibility for resecting newly diagnosed stage I NPCs, and subsequent studies have identified specific patient populations who stand to benefit most from such procedures. A prospective clinical trial (NCT03353467) is currently underway to rigorously evaluate the efficacy and safety of endoscopic surgery for stage I NPC, underscoring the growing momentum behind this therapeutic avenue.
Addressing Surgical Challenges with NESD
Despite the advancements in ENPG, certain anatomical complexities, particularly tumors located in the pharyngeal recess and the lateral wall of the nasopharynx, presented ongoing challenges. The narrow confines of the nasal and nasopharyngeal cavities, coupled with the critical proximity of vital structures like the internal carotid artery (ICA), demanded highly specialized surgical skills and a deep understanding of regional anatomy. To overcome these hurdles, a series of innovative techniques have been developed and integrated into endoscopic nasopharyngeal surgery. These include the "third-hand technique," which enhances instrument manipulation; "cube-like resection," a method for achieving complete tumor removal; the "dumpling-making technique," likely referring to a method of specimen handling; and the "pedicle nasal mucoperiosteal flap," used for reconstruction. These innovations have aimed to facilitate en bloc resection of tumors, ensure protection of the ICA, and effectively reconstruct surgical defects.
However, the pursuit of an optimal surgical perspective, enhanced anatomical clarity, and standardized procedures remains a constant endeavor. The delicate balance between achieving radical tumor resection and minimizing the risk of ICA injury has been a paramount concern. It is within this evolving landscape that the Nasopharyngeal Endoscopic Submucosal Dissection (NESD) technique has been developed. NESD represents a significant evolution, designed to enable the safe and complete resection of the entire nasopharyngeal mucosa, encompassing challenging areas like the pharyngeal recess and lateral wall, while providing superior protection to the ICA. This article marks the first report of initial surgical experiences utilizing the NESD technique for localized early-stage NPC.
Case Study: A Pioneer in NESD Treatment
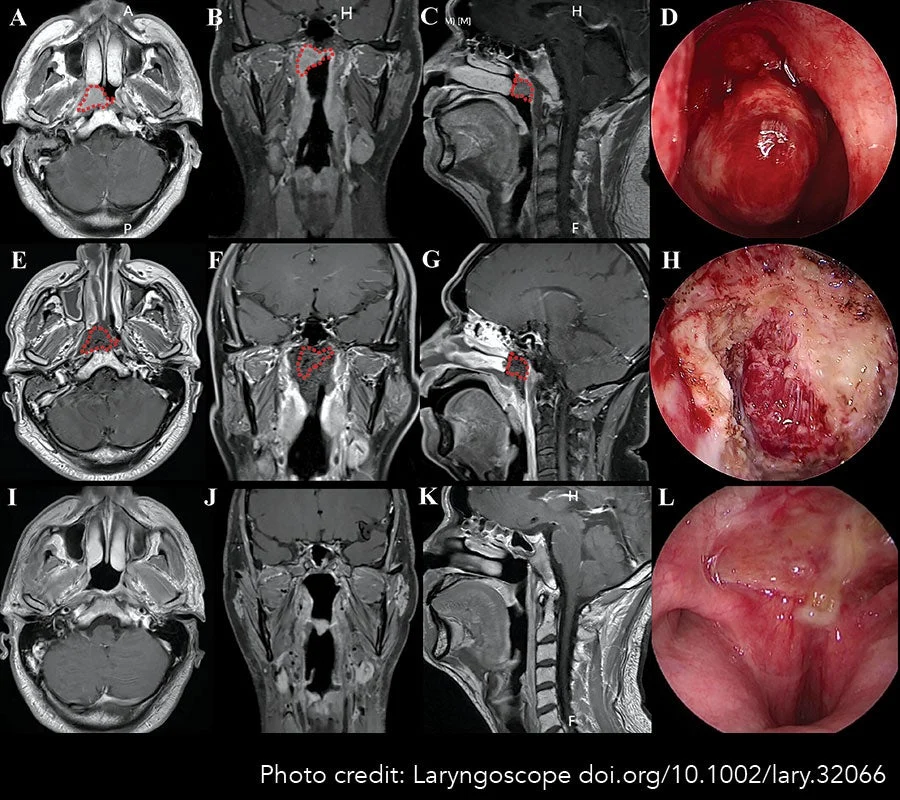
The application of NESD was recently demonstrated in a case involving a 40-year-old male patient who was incidentally diagnosed with an undifferentiated nonkeratinizing carcinoma during a routine health examination. The neoplasm was identified on the right and posterior walls of his nasopharynx. A comprehensive diagnostic workup, including magnetic resonance imaging (MRI), positron emission tomography-computed tomography (PET-CT), and endoscopy, was conducted to meticulously assess the extent of tumor invasion. Based on the eighth edition of the Union for International Cancer Control (UICC) staging system, the patient was diagnosed with T1N0M0 stage I NPC.
Following thorough consultation and discussion of treatment options, including radiotherapy, the patient opted for the NESD procedure. This decision was informed by the desire for a less invasive approach with potentially fewer long-term side effects. The planned surgical margins were meticulously defined to encompass the entire nasopharyngeal mucosa, guided by pre-operative MRI scans which clearly delineated the gross tumor volume on the right and posterior nasopharyngeal walls. The study protocol received approval from the Clinical Research Ethics Committee of the Fifth Affiliated Hospital of Guangzhou Medical University, and the patient provided written informed consent for his participation and the use of his anonymized data.

The NESD Surgical Procedure: A Step-by-Step Innovation
The NESD procedure was performed under general anesthesia. Following standard pre-operative preparation and draping, nasal endoscopy was utilized to apply a vasoconstrictive agent (1:10,000 epinephrine) to the nasal mucosa, facilitating improved visualization and reduced bleeding during the endoscopic approach.
The nasopharyngeal cavity, visualized endoscopically, was conceptualized as a roughly "cube-shaped" space. The tumor, precisely located on the right and posterior walls, served as the primary target for resection. The NESD technique, executed via an oronasal approach using a 4-mm rigid endoscope, involved a carefully orchestrated seven-step process designed for the comprehensive removal of the entire nasopharyngeal mucosa.
Step 1: Resection Boundary Marking: The initial phase involved precise marking of the planned resection boundaries around the nasopharyngeal cavity using electrocoagulation. This step ensured accurate guidance for subsequent dissection.
Step 2: Anterior Wall Mobilization: The anterior wall of the nasopharynx was freed. This involved incising the posterior mucosa of the nasal septum and carefully polishing the vomer bone. This maneuver was crucial for expanding the surgical operating space within the nasopharynx.
Step 3: Superior Wall Excision: The superior wall of the nasopharynx was then excised. This required meticulous separation of the entire superior nasopharyngeal wall from the upper margin of the posterior nostril, extending along the bony surface towards the clivus.
Step 4: Establishing the Trans-Oral-Nasal Approach (TONA): A critical step in enhancing the surgical view and access involved establishing the TONA. A mouth gag was employed to keep the patient’s mouth open. Two catheters were then strategically inserted through the bilateral nasal cavities and into the oropharyngeal cavity, with their tips being exteriorized from the oral cavity. This innovative suspension of the soft palate, facilitated by the TONA approach, significantly broadened the surgical perspective, created a more spacious operating environment, and streamlined surgical pathways.
Step 5: Posterior Wall Separation and Safety Tunnel Creation: The posterior wall was carefully separated. A crucial element of this step was the creation of a "safety tunnel" between the nasopharyngeal mucosa and the underlying musculature. The mucosa of the posterior nasopharyngeal wall was incised and meticulously separated along the surface of the longus capitis muscle, extending towards the pharyngeal raphe. Throughout this dissection, the integrity of the longus capitis muscle membrane was rigorously maintained. Subsequently, the loose connective tissue within the submucosal space at the junction of the posterior and lateral nasopharyngeal mucosal walls was carefully dissected, extending towards the apex of the petrous portion of the temporal bone and the inner aspect of the internal carotid artery (ICA) sheath. This meticulous dissection established a safe tunnel, effectively separating the nasopharyngeal mucosa from the vital ICA region. The connective tissue was then excised inward and upward until it met the superior wall incision.
Step 6: Left Lateral Wall Excision: The left lateral wall of the nasopharynx was then excised. The mucosa at the midpoint of the left Eustachian tube carina was incised, and the mucosal tissue was separated along the submucosal space towards the parapharyngeal space. The pharyngeal recess was carefully dissected until the deepest corner of the established safety tunnel was reached. These incisions were then converged with the nasopharyngeal superior and posterior wall incisions to achieve complete excision of the left nasopharyngeal wall. Extreme care was exercised to remain within the boundaries of the safety tunnel, thereby preventing injury to the parapharyngeal vessels and nerves.
Step 7: Right Lateral Wall Excision: The right lateral wall was excised utilizing an analogous technique to the left side, involving the establishment of a right-sided safety tunnel. The mucosa of the right Eustachian tube carina was divided and separated into the right recess through the submucosal space. This dissection converged with the contralateral nasopharyngeal superior and posterior wall incisions, extending along the surface of the longus capitis muscle. This final step ensured that the entire nasopharyngeal mucosa was completely dissociated from the tumor.

The entire specimen, comprising the tumor encased within the whole nasopharyngeal mucosa, was then removed orally as a single en bloc unit. This ensured that the tumor was excised with adequate safe margins. Post-operative imaging confirmed the complete removal of the primary tumor and the entire nasopharyngeal submucosa.
Following the complete resection, meticulous hemostasis was achieved. The operative cavity was irrigated with distilled water to mitigate the risk of tumor cell implantation. Multiple biopsies were taken from the margins of the resection site for pathological examination to confirm negative margins. A bioresorbable film was then applied to cover the nasopharyngeal wound, promoting reepithelialization. A gelatin sponge and absorbable fibrin glue were used to fill the operative cavity, providing support and aiding in hemostasis. A final intraoperative assessment confirmed the absence of active bleeding in the oropharynx or bilateral nostrils.
Post-Operative Management and Follow-Up
Post-operative management involved regular endoscopic assessments of the wound every two weeks until complete reepithelialization was achieved. A structured follow-up protocol was implemented: assessments were scheduled every three months for the first three years, every six months from the fourth to fifth year, and annually thereafter. Each follow-up included nasopharyngoscopy, head and neck MRI, and quantitative measurement of Epstein-Barr virus (EBV)-DNA copy numbers, a key biomarker for NPC. Conventional examinations such as chest X-rays and abdominal ultrasounds were performed every six to 12 months, with more comprehensive whole-body imaging, including skeletal scintigraphy or PET/CT, reserved for cases where clinically indicated.
Remarkable Outcomes and a Promising Prognosis
The surgical procedure for this patient was completed within 130 minutes, with an estimated blood loss of only 50 mL. Crucially, the patient experienced no post-operative complaints of headache or nosebleeds. Within a week of surgery, post-operative MRI scans unequivocally demonstrated the complete removal of the primary tumor and the entire nasopharyngeal submucosa, with no residual disease evident.
Pathological examination of the margin biopsies confirmed negative margins, signifying a successful oncological resection. The surgical wound demonstrated complete healing within three weeks. Over a comprehensive two-year follow-up period, the patient remained disease-free, with no evidence of tumor recurrence or progression. Furthermore, he did not experience any significant sequelae commonly associated with traditional treatments, such as dry mouth, deafness, otitis, trismus (difficulty opening the mouth), dysphagia (difficulty swallowing), or nasal obstruction. These favorable outcomes underscore the potential of NESD as a safe and effective organ-preserving treatment for early-stage NPC.
Broader Implications and Future Directions
The successful application of NESD in this case represents a significant stride forward in the minimally invasive management of stage I nasopharyngeal carcinoma. The technique’s ability to achieve complete mucosal resection with meticulous protection of vital structures, particularly the ICA, addresses a long-standing surgical challenge. As the number of early-stage NPC diagnoses continues to rise, NESD offers a compelling alternative to radiotherapy, potentially leading to improved quality of life for patients by mitigating the risk of treatment-related morbidities.
The development of NESD, building upon earlier endoscopic techniques, highlights the continuous innovation within head and neck surgical oncology. The systematic, multi-step approach described in this procedure suggests a pathway toward standardization, which is crucial for wider adoption and consistent patient outcomes.
Further research and larger prospective studies are warranted to definitively establish the long-term oncological efficacy, safety profile, and cost-effectiveness of NESD compared to conventional radiotherapy and other endoscopic approaches. However, this initial report provides strong evidence that NESD holds considerable promise as a refined, minimally invasive surgical solution for carefully selected patients with early-stage nasopharyngeal carcinoma, paving the way for a new era of precision oncology in the nasopharynx.