The Role of the Cerebellum in Multiple Sclerosis
Multiple sclerosis (MS) is traditionally characterized by the immune system’s misguided attack on myelin, the protective sheath that insulates nerve fibers. When myelin is stripped away—a process known as demyelination—the transmission of electrical impulses is disrupted, leading to symptoms ranging from cognitive impairment to complete loss of motor function. In approximately 80% of clinical cases, the disease involves significant inflammation within the cerebellum.
Located at the back of the brain, the cerebellum—Latin for "little brain"—is responsible for the "fine-tuning" of motor activity. While the motor cortex initiates movement, the cerebellum ensures that those movements are smooth, coordinated, and balanced. It is the region that allows a person to walk a straight line, reach for a glass without overshooting, or maintain posture. When the cerebellum is compromised, patients often experience ataxia, a condition marked by slurred speech, stumbling, and a lack of coordination that mimics alcohol intoxication.
The UCR research, led by Seema Tiwari-Woodruff, a professor of biomedical sciences, and graduate researcher Kelley Atkinson, suggests that the physical decline in MS is not merely a result of "broken wires" (demyelination) but is exacerbated by a fundamental energy crisis within the neurons themselves.
The Energy Crisis: Mitochondrial Failure and Purkinje Cells
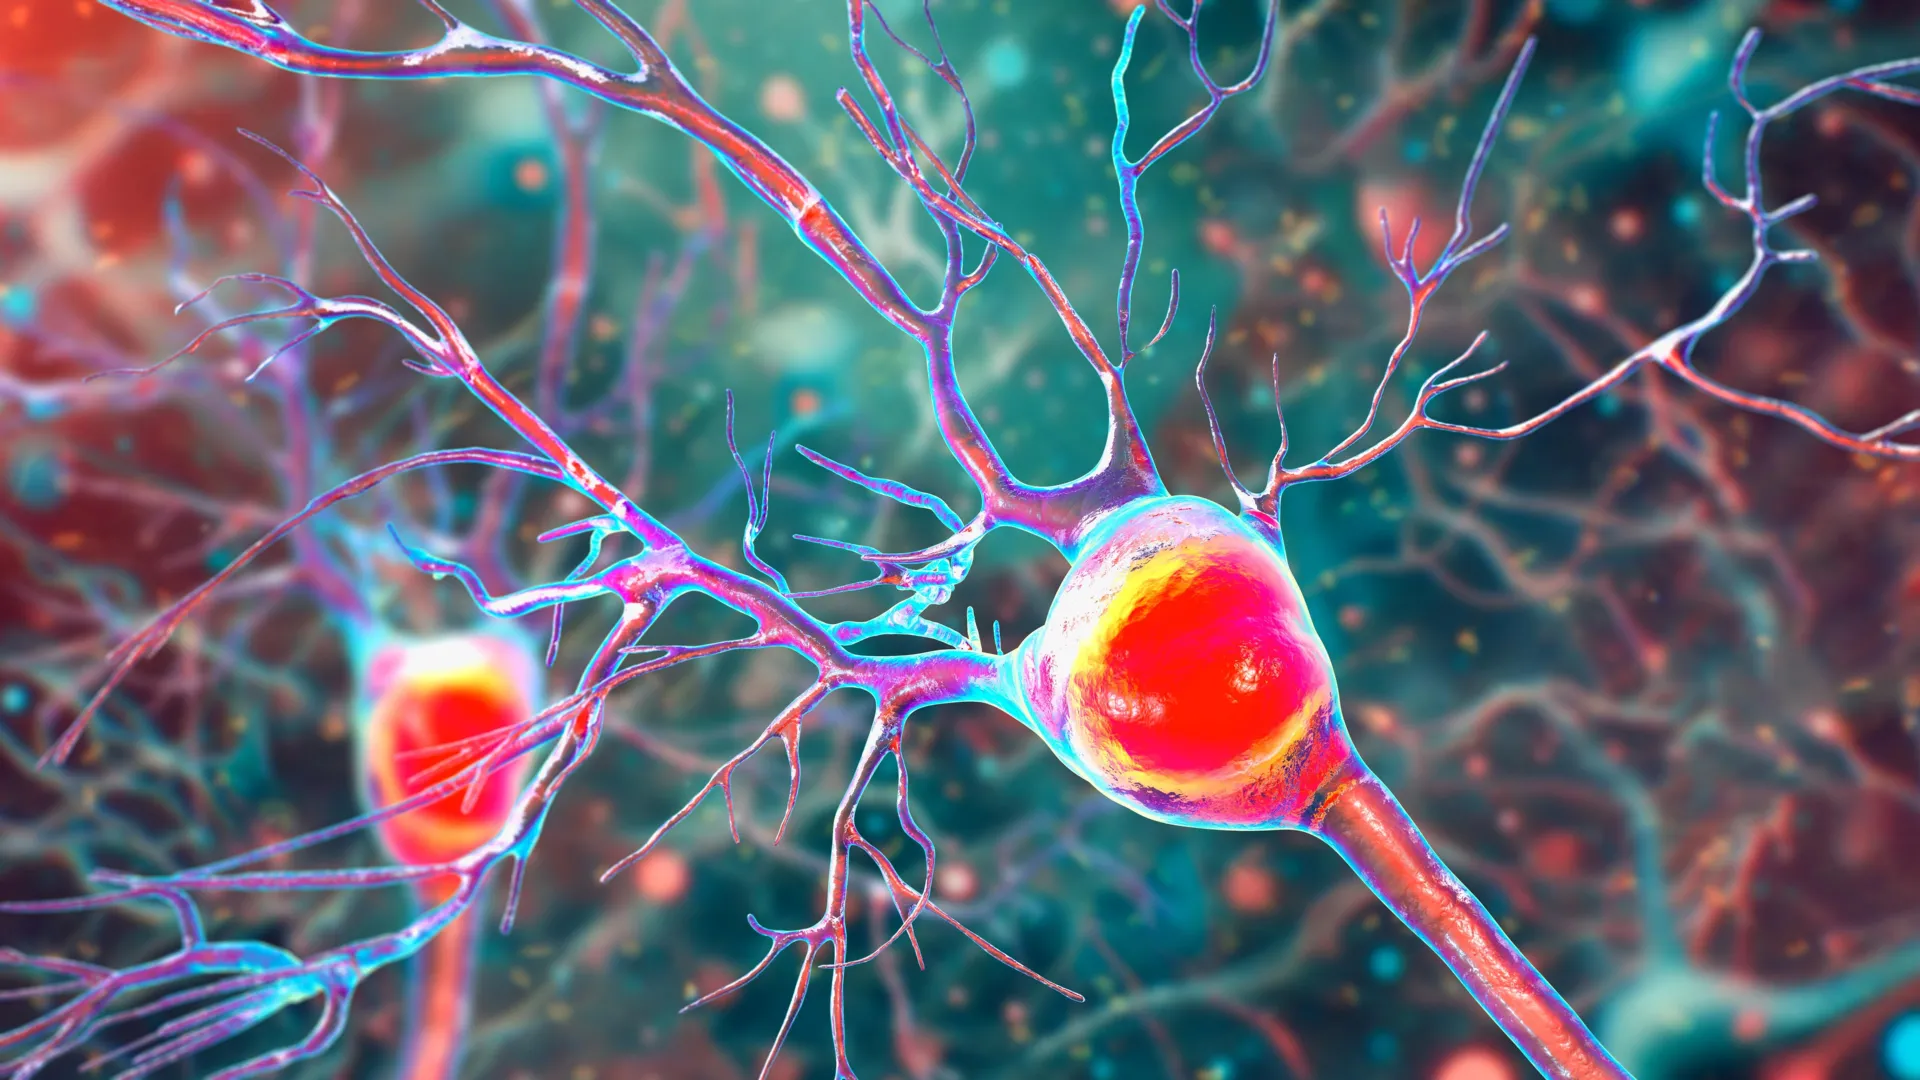
At the heart of the UCR study are Purkinje cells, some of the largest and most complex neurons in the human brain. These cells are the primary output neurons of the cerebellar cortex; they integrate vast amounts of sensory information and send inhibitory signals that regulate motor movement. Because of their massive size and high firing rates, Purkinje cells have immense metabolic demands. They require a constant, robust supply of adenosine triphosphate (ATP), the chemical energy currency of the cell.
Mitochondria are the organelles responsible for producing this energy. In the healthy brain, mitochondria are distributed throughout the Purkinje cell to power its intricate dendritic branches. However, the UCR team discovered that in the context of MS-related inflammation and demyelination, these mitochondria begin to malfunction. Specifically, the researchers observed a significant reduction in the mitochondrial protein COXIV (Cytochrome c oxidase subunit 4). COXIV is a key component of the electron transport chain, the final stage of aerobic respiration. Without sufficient COXIV, the mitochondria cannot produce enough energy to maintain the cell’s structural integrity or its electrical activity.
Professor Tiwari-Woodruff noted that the loss of this protein appears to be a harbinger of cell death. As energy production fails, the Purkinje cells lose their dendritic branches—the "arms" they use to communicate with other neurons—and eventually undergo apoptosis, or programmed cell death. This loss is irreversible, leading to the permanent disability often seen in progressive forms of MS.
Comparative Analysis: Human Pathology and the EAE Model
To reach these conclusions, the research team employed a dual-track methodology, analyzing both human postmortem tissue and an established animal model. The human samples were obtained from the National Institutes of Health (NIH) NeuroBioBank and the Cleveland Clinic, focusing on individuals who had been diagnosed with secondary progressive MS (SPMS). SPMS is a stage of the disease where disability increases steadily, regardless of the presence of relapses.
The analysis of human cerebellar tissue confirmed a stark reality: in areas where demyelination was most severe, Purkinje cell density was significantly lower. The remaining cells showed clear signs of metabolic stress, including stunted branching and depleted mitochondrial proteins.
To observe the chronology of this decline, the researchers utilized the experimental autoimmune encephalomyelitis (EAE) mouse model. EAE is the gold standard in MS research because it mimics the inflammatory and demyelinating aspects of the human disease. By tracking the mice over a period of several weeks, the team was able to establish a timeline of neurodegeneration:
- Early Phase: Inflammation begins in the central nervous system, and the immune system starts attacking the myelin sheaths in the cerebellum.
- Intermediate Phase: While the neurons are still alive, mitochondrial function begins to drop. The levels of COXIV decrease, and the cells’ ability to produce energy is compromised.
- Late Phase: The energy-starved Purkinje cells begin to die off. This correlates with the onset of severe motor deficits in the mice, such as tail paralysis and hind-limb weakness.
This timeline is crucial because it suggests a "window of opportunity" for medical intervention. If the energy failure occurs before the actual death of the neuron, there may be a chance to intervene and save the cell.
Broadening the Scope: Glial Cells and Future Research
While the current study focuses heavily on Purkinje cells, the UCR team is already expanding its investigation into the roles played by other cerebellar cells. Neurodegeneration does not happen in a vacuum; neurons rely on a supporting cast of glial cells to survive.
One area of interest is the oligodendrocyte. These are the cells responsible for creating and maintaining the myelin sheath. If mitochondria are failing in Purkinje cells, it is highly likely they are also failing in oligodendrocytes, which would prevent the brain from repairing damaged myelin (remyelination). Additionally, the researchers are looking at astrocytes, which provide nutritional support to neurons and help regulate the chemical environment of the brain.
"Targeting mitochondrial health may represent a promising strategy to slow or prevent neurological decline," Tiwari-Woodruff explained. The implication is that future MS therapies might need to be "cocktails" that combine traditional immunosuppressants—to stop the initial attack—with neuroprotective agents designed to boost mitochondrial efficiency or stabilize energy production.
Clinical Implications and the Economic Burden of MS
The findings come at a time when the economic and social costs of MS are under increasing scrutiny. According to the National Multiple Sclerosis Society, which funded this study, the total economic burden of MS in the United States exceeds $85 billion annually. This includes direct medical costs as well as indirect costs like lost wages and the need for long-term care.
A significant portion of these costs is driven by the transition from relapsing-remitting MS to progressive MS. While current disease-modifying therapies (DMTs) are highly effective at reducing the frequency of relapses, they are often less effective at halting the slow, "smoldering" progression of the disease that leads to permanent wheelchair use and loss of independence. By identifying mitochondrial failure as a key driver of this progression, the UCR study provides a new target for drug development that specifically addresses the needs of patients with progressive forms of the disease.
A Call for Sustained Research Funding
The complexity of the brain and the multifaceted nature of MS require long-term, intensive scientific inquiry. Professor Tiwari-Woodruff used the publication of this study to emphasize the necessity of public and private investment in basic science. She argued that understanding the molecular "nuts and bolts" of how cells die is the only way to move beyond symptomatic treatment toward actual cures.
"Cutting funding to science only slows progress when we need it most," Tiwari-Woodruff stated. The sentiment reflects a broader concern in the scientific community regarding the volatility of research grants and the impact that funding gaps can have on multi-year studies like the one conducted at UC Riverside.
Conclusion: A New Frontier in MS Treatment
The discovery that mitochondrial impairment in the cerebellum is a direct contributor to Purkinje cell loss marks a significant shift in how researchers view MS pathology. It moves the conversation from a purely immunological perspective—where the focus is on the "attacker" (the immune system)—to a neurobiological perspective that focuses on the "victim" (the neuron and its energy supply).
As the UCR team moves forward with their research into other cell types and potential therapeutic compounds, the goal remains clear: to preserve the quality of life for those living with MS. For a patient, the difference between mitochondrial failure and mitochondrial health could be the difference between losing the ability to walk and maintaining the coordination needed for daily life. This research brings the medical community one step closer to a future where multiple sclerosis is no longer a path toward inevitable physical decline, but a manageable condition where the brain’s powerhouses are kept running.