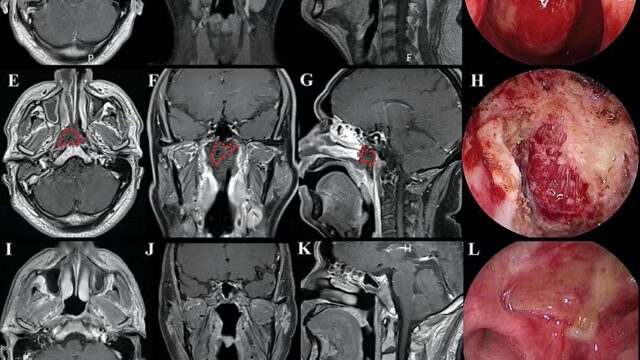
The patient and his wife, understandably anxious, sought a rapid diagnosis. In response, the physician provided a comprehensive list of potential diagnoses, with a space-occupying mass at the forefront. Inquiring about Mr. Bell’s long-standing career as a gunsmith, spanning over three decades, the physician recommended a CT scan of the sinuses for further diagnostic evaluation. Given the patient’s residence over 200 miles away, a plan was made to communicate the scan results via telephone upon the physician’s return from an out-of-state family wedding the following week.
Unbeknownst to the physician, Mr. Bell registered for the practice’s patient portal. Two days after the imaging, he discovered a newly uploaded radiology report. The report stated: "Sinonasal mass with bone erosion of anterior and superior right maxillary sinus walls with involvement of the right nasal cavity. The most likely diagnosis is a squamous cell carcinoma with osseous erosion." This stark, uncontextualized diagnosis, encountered through an automated system, understandably sent Mr. Bell into a state of distress, prompting an immediate call to the physician’s office demanding a callback. Upon receiving the call, Mr. Bell expressed his anger and fear, stating, "You should have called me right away after you received the report. I have no idea what this report means for my life other than what I read in internet searches. Am I going to die soon?"
This incident highlights a growing ethical dilemma in modern healthcare: the rapid dissemination of potentially life-altering medical information through patient portals, often without the crucial layer of human interpretation and emotional support. While patient access to their medical data is a cornerstone of patient autonomy, the unmediated delivery of sensitive results raises significant concerns about communication, understanding, and the very nature of the physician-patient relationship.
The Communication Divide: Access vs. Understanding
The core of the ethical challenge lies not in whether patients have a right to their medical information—they unequivocally do—but whether an electronic system, by merely transmitting accurate data swiftly, fulfills the ethical obligations of medicine. The distinction between "access" and "communication" is critical. A patient portal can efficiently deliver a pathology or radiology report, but it cannot, by itself, reliably gauge patient comprehension, correct misinterpretations, explain inherent uncertainties, answer nuanced questions, assess emotional responses, or contextualize the findings within the patient’s unique clinical history and life circumstances.
Professional ethics guidance underscores this distinction. The American Medical Association’s Code of Medical Ethics Opinion 2.1.5 emphasizes that patients should receive clinical test results within a reasonable timeframe, conveyed sensitively and understandably, and with sufficient information to make informed decisions. The code further recommends that patients be informed about when and how they can expect results, and crucially, that the ordering physician be notified and have access to any information disclosed directly by a third party. This clearly indicates that the ethical duty extends beyond mere data transmission.
Navigating Autonomy and Beneficence in the Digital Age
The ethical quandary should not be framed as a dichotomy between disclosure and secrecy. Instead, the focus must shift to preserving transparency while simultaneously upholding patient preferences and the physician’s indispensable interpretive role. The ultimate ethical objective of medicine—informed understanding—is intrinsically linked to the four pillars of medical ethics: autonomy, beneficence, nonmaleficence, and social justice.
Respect for autonomy strongly advocates for patients’ unfettered access to their health information. Immediate patient portal access can indeed streamline healthcare, reducing reliance on cumbersome office workflows, eliminating unnecessary waiting periods, enabling patients to formulate pertinent questions, facilitating second opinions, and fostering active participation in their care. Any attempt to reintroduce routine physician-controlled withholding of results would directly contravene contemporary patient expectations and the ethical rejection of paternalistic approaches.

However, autonomy is not synonymous with unbridled speed. True respect for autonomy entails honoring a patient’s informed preferences, which encompass the timing, mode, and circumstances of disclosure. The same patient who might desire immediate access to a lipid panel result could reasonably prefer not to receive a new cancer diagnosis via an automated push notification while alone at night. A patient can autonomously opt for immediate disclosure, while another can autonomously choose clinician-mediated disclosure. The ethically significant factor is not uniform delivery but rather that patients retain meaningful control over how they receive information that may have profound implications for their lives.
Otolaryngologists, in particular, must approach the immediate access of test results with caution, while also acknowledging the potential harms of delayed communication. Many patients find rapid results reassuring rather than distressing, and prolonged waiting can foster significant anxiety. Furthermore, patients who lack independent access to their records may miss abnormal findings or delay necessary follow-up. Therefore, the ethical principle of nonmaleficence cannot be invoked as an overarching justification for withholding information.
The Peril of Uninterpreted Data
Medical reports, by their nature, are primarily intended for clinical communication among healthcare professionals. They often contain specialized terminology, preliminary differential diagnoses, probabilistic statements, and descriptive language that carries meanings distinct from their everyday usage. Terms such as "suspicious," "cannot exclude," "positive margin," or "indeterminate," or even automatically flagged laboratory values, can be readily misinterpreted by patients as definitive pronouncements of prognosis when, in reality, they are often preliminary or require further clinical correlation.
The pertinent ethical question is not whether clinicians should prevent all patient anxiety, an impossible and sometimes counterproductive goal, but rather whether healthcare systems should knowingly impose avoidable anxiety by separating consequential information from adequate opportunities for explanation and support. The principle of beneficence compels the design of systems that empower and support patients while mitigating predictable and remediable harms.
The otolaryngologist’s responsibility does not diminish once a patient portal releases a report. In fact, the ease of electronic transmission amplifies the imperative to distinguish the health system’s technical act of data delivery from the clinician’s professional duty to communicate. Patients place their trust in physicians not merely to order tests but to interpret their meaning, articulate uncertainties, recommend subsequent steps, and provide steadfast support, especially when the news is distressing. Consequently, a system can be informationally transparent yet communicatively deficient. Fidelity to the patient demands that physicians and health systems refrain from equating portal availability with meaningful disclosure.
Addressing Health Literacy and Equity
Unsupported portal disclosure also raises significant concerns related to social justice. Patients exhibit a wide spectrum of health literacy, English proficiency, numeracy skills, cognitive capacities, access to reliable internet resources, and familiarity with medical terminology. A highly educated clinician might perceive a report as self-explanatory, while a patient may encounter an unfamiliar lexicon of alarming words. The burden of translating specialized medical language into comprehensible information should not be unilaterally shifted from the healthcare professional to the patient.
The growing tension surrounding this issue has prompted legislative action in some jurisdictions. Texas, for instance, enacted legislation effective September 1, 2025, prohibiting the electronic disclosure of certain "sensitive test results"—including pathology or radiology reports reasonably likely to indicate malignancy and tests that may reveal a genetic marker—prior to the third day after their finalization. This legislation, while potentially introducing mandatory delays, underscores a societal recognition of a qualitative difference between routine data access and the electronic delivery of potentially life-altering diagnoses.
However, national ethics guidance should exercise caution in replacing one rigid rule with another. Mandatory delays, while protective for some, may frustrate patients who strongly prefer immediate access and could introduce risks if clinical follow-up is delayed. A more ethically robust approach would involve building systems around informed patient preference and supported disclosure, rather than universal embargoes.
The Case for Supported Release
The most ethically sound approach likely lies in a model of "supported release"—neither unrestricted automated dissemination nor routine physician-controlled withholding. This model would preserve timely access while deliberately surrounding consequential information with preparation, patient choice, contextualization, and dependable clinician follow-up.

Practical elements of such a model could include:
- Proactive Patient Education: Educating patients about the practice’s protocol for releasing test results through the portal, including what types of results are typically released and the anticipated timeline for interpretation and discussion.
- Opt-in Mechanisms for Sensitive Results: Allowing patients to actively choose how and when they receive sensitive test results, such as opting for a phone call or in-person discussion before the report appears on the portal.
- Timely Physician Review and Annotation: Ensuring that physicians promptly review and, where appropriate, annotate portal results with brief explanations or context before they are visible to the patient.
- Integrated Communication Tools: Developing portal features that facilitate direct, secure communication between patients and clinicians for quick clarification of preliminary findings.
- Pre-Appointment Preparation: For significant or potentially sensitive tests, scheduling a brief follow-up appointment or telehealth visit shortly after the anticipated result availability to discuss findings.
Otolaryngologists frequently order tests with reports that can carry immense emotional weight, even before a complete diagnostic picture emerges. This includes neck mass cytology, surgical pathology, temporal bone and skull base imaging, thyroid and salivary gland biopsies, genetic testing, hearing and vestibular studies, and radiographic evaluations for recurrent malignancy. The specialty is therefore acutely exposed to the divergence between a technically accurate report and a clinically meaningful explanation.
A pathology report confirming squamous cell carcinoma, for example, may merely be the initial step in a complex diagnostic journey. Critical aspects such as HPV association, primary site identification, tumor burden, staging, surgical candidacy, radiation options, functional consequences, and prognosis may remain unresolved. Similarly, an MRI might identify a "mass," "enhancement," or "possible recurrence" that necessitates comparison with prior studies or multidisciplinary review for definitive interpretation. While immediate release of the raw data might be feasible, immediate interpretation cannot always be automated.
Conclusion: Towards Meaningful Transparency
The patient portal represents a significant advancement in healthcare transparency and patient engagement. The ethical response to its unintended consequences should not involve reverting to physician ownership of medical information. Nor should medicine embrace the extreme opposite: that the fastest possible electronic transmission of data absolves the professional duty to communicate.
A more ethically defensible position is that immediate access to information should generally be maintained, but the unsupported release of consequential information should not be considered an adequate model of patient-centered care. Patients should be prepared for how results will be delivered via the portal, be afforded meaningful control over notification and timing where feasible, and be provided with timely access to clinical interpretation.
In Mr. Bell’s case, a robust patient-physician relationship, built on trust and honesty, is paramount. The journey ahead in managing his tumor will be long, and positive communication, characterized by active listening, can serve as the foundational element for this crucial relationship.
A computer can transmit a result, but it cannot assume the physician’s responsibility to help a patient comprehend what that result signifies for their life. Therefore, the ethical success of the patient portal should be measured not solely by the speed at which information reaches a patient’s screen, but by whether the patient becomes more informed rather than merely more alarmed. Transparency devoid of interpretation can leave a patient technically informed yet profoundly alone, a state antithetical to excellence in patient care. We treat not only the patient, but also the person.