


Understanding the Four Stages of Meniere’s Disease
Meniere’s disease is often conceptualized through four broad stages: early, middle, late, and advanced. These are descriptive rather than diagnostic categories, intended to illustrate common patterns of symptom progression. However, individual experiences can diverge significantly; not everyone progresses through all stages, and symptoms do not always follow a predictable sequence.
In the initial phases, symptoms may be intermittent, characterized by sudden vertigo, tinnitus, ear pressure, and hearing fluctuations that improve between episodes. As the disease advances, vertigo might decrease in frequency, but hearing loss, tinnitus, and balance issues can become more persistent and permanent.
Examples of Symptom Patterns Associated with the Four-Stage Model:

| Stage | Vertigo | Hearing Loss | Tinnitus/Fullness | Balance |
|---|---|---|---|---|
| Early | Sudden, intense attacks (20 mins to hours) | Fluctuating, may normalize between episodes | Ringing, ear fullness | Usually normal |
| Middle | Less frequent or less severe | More persistent, less recovery between episodes | More constant tinnitus/pressure | Mild imbalance begins |
| Late | Less frequent or less severe | Significant and more permanent | Ongoing tinnitus/fullness | Persistent imbalance |
| Advanced | Rare or absent (Burnout phase) | Permanent, often severe | Constant tinnitus/fullness | Ongoing imbalance |
Important Note: This table illustrates common symptom patterns. Individual progression can vary, and symptoms may overlap or follow a different course.
Stage 1: Early Stage – The Onset of Symptoms
The early stage of Meniere’s disease is often marked by fluctuating and unpredictable symptoms. Individuals may experience sudden vertigo attacks, creating a sensation of the room spinning. Alternatively, the initial signs could be changes in hearing, tinnitus, aural fullness, dizziness, or a general sense of imbalance.
Hearing loss at this stage typically fluctuates, meaning it can be muffled or reduced during an episode and then improve afterward. Tinnitus, often described as a ringing, buzzing, or humming sound in the ear, is also common. Aural fullness, feeling pressure, blockage, or congestion in the affected ear, is another prevalent symptom. The intermittent nature of these symptoms can lead to confusion, with individuals sometimes attributing them to stress, fatigue, migraines, or ear infections.
To aid in diagnosis and treatment discussions, tracking symptoms diligently is recommended. This involves noting the timing, duration, and characteristics of vertigo attacks, as well as any changes in hearing, tinnitus, or ear fullness.
Stage 2: Middle/Intermediate Stage – Increased Impact on Daily Life
In the middle stage, symptoms often become more noticeable and begin to impact daily life more significantly, though individual experiences vary. Vertigo attacks may continue, though some individuals report they become less frequent or less severe. However, others continue to experience unpredictable episodes.

Hearing loss tends to become more persistent, with less complete recovery between attacks. Tinnitus may become more constant, and the sensation of ear fullness can last longer. Communication can become more challenging, with difficulties in noisy environments, following conversations in groups, or understanding speech on the affected side. The interplay of hearing and balance issues can also lead to mild unsteadiness between attacks.
While periods of remission can still occur, symptoms in this stage may feel less transient and more like an ongoing aspect of daily life compared to the early stage.
Stage 3: Late Stage – Persistent Hearing and Balance Challenges
During the late stage of Meniere’s disease, vertigo attacks often decrease in frequency or intensity. This reduction in vertigo does not necessarily signify an improvement in the overall condition. Instead, the primary challenges may shift towards more permanent hearing loss and balance problems.
Hearing loss in the affected ear can become significant and persistent. Tinnitus may continue, and some individuals still experience ear fullness or pressure. Balance can become considerably more difficult, particularly in low light, on uneven surfaces, or when fatigued. This can impact confidence and independence, leading some to avoid activities like crowded places, driving, or navigating stairs due to the risk of sudden balance disturbances. Support from ENT specialists, audiologists, and balance therapists becomes crucial for developing practical coping strategies.
Crucial Insight: A decrease in vertigo episodes does not automatically equate to recovery. In later stages, persistent long-term hearing and balance changes can remain even if vertigo attacks are less frequent.
Stage 4: Advanced Stage (Burnout Phase) – Long-Term Sequelae
The advanced stage is sometimes referred to as the "burnout phase." This typically signifies a reduction or cessation of vertigo attacks, while the long-term inner ear damage persists. However, this specific pattern is not universal, and this stage is not universally defined as a distinct phase of Meniere’s Disease.
At this point, hearing loss in the affected ear can be permanent and severe. Tinnitus and ear fullness may also persist. Balance problems can remain due to the inner ear’s reduced ability to send reliable balance signals. In some individuals, sudden falls known as "drop attacks" can occur without loss of consciousness or warning, posing a significant risk of injury and requiring immediate medical attention.
Timeline and Progression: A Fluid Concept
There is no fixed timeline for the progression through the four stages of Meniere’s disease. Some individuals experience fluctuating symptoms for many years, while others develop more persistent hearing loss or balance issues over time. Crucially, not everyone will experience all four stages, and symptoms can overlap, appearing concurrently from different stages.
The variability in symptom presentation is a hallmark of Meniere’s disease. Periods of remission are common, making the condition difficult to predict. The four-stage model serves best as a simplified framework for understanding potential symptom evolution, rather than a rigid pathway. Regular follow-ups with an ENT specialist or audiologist are essential for monitoring symptoms and adjusting treatment accordingly.
Understanding the Phases of an Attack
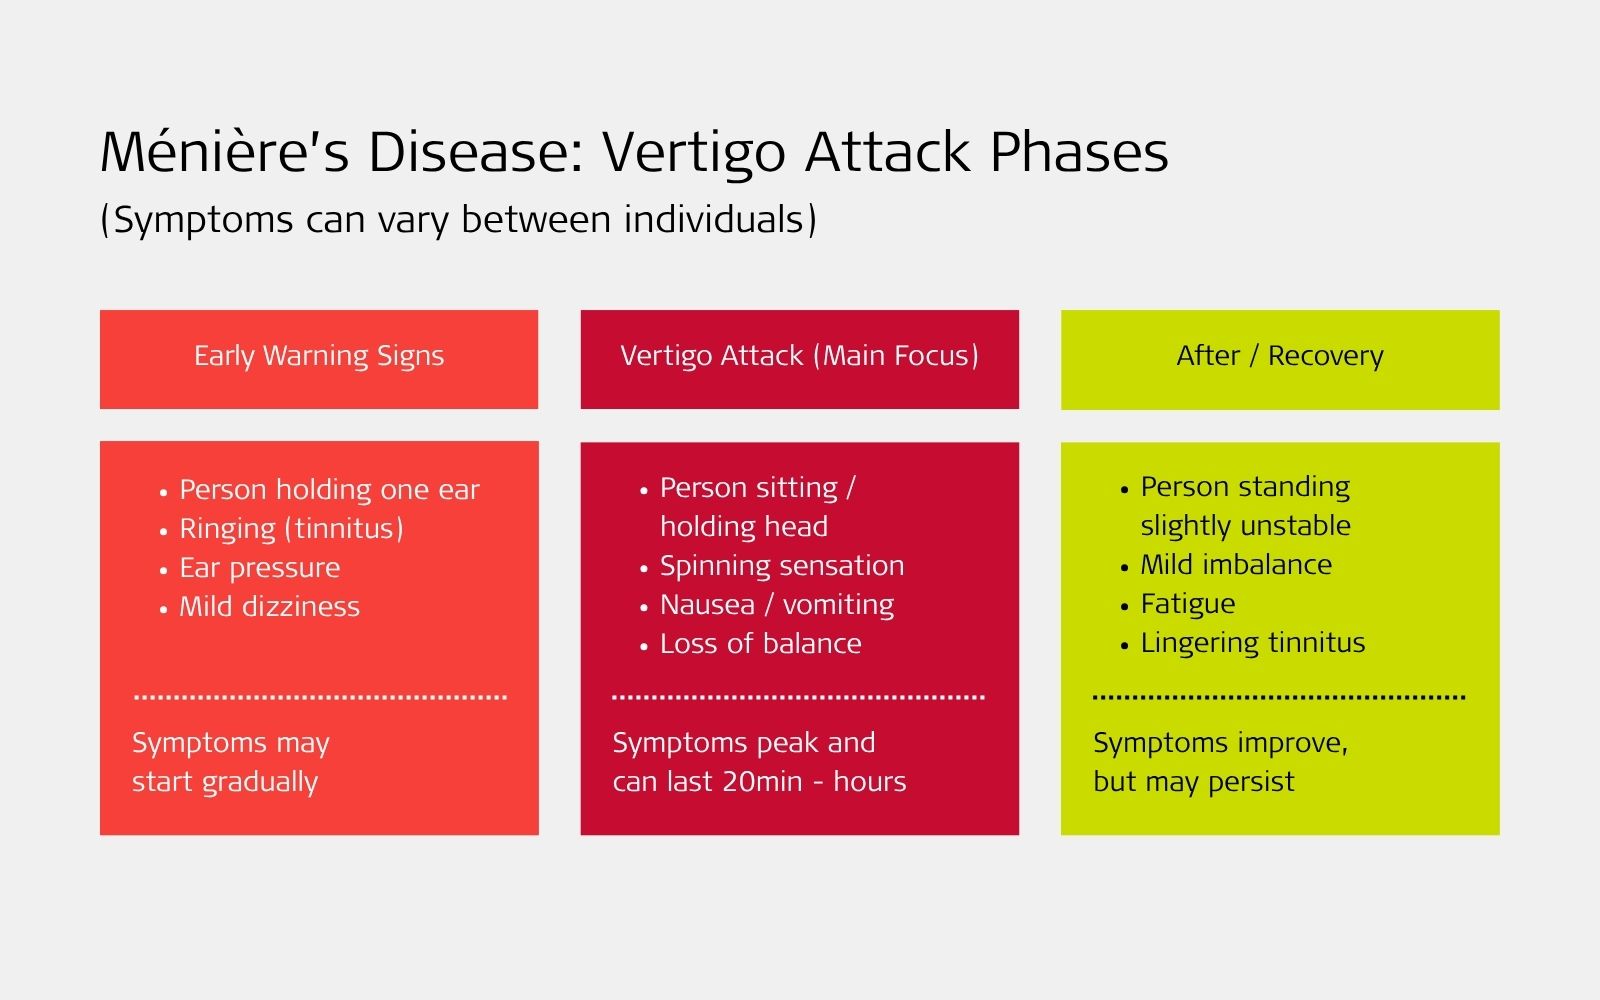
Meniere’s disease symptoms often manifest in episodes, rather than being constant. Many individuals describe a pattern involving early warning signs, the active symptom phase, and a recovery or remission period. However, the experience of these phases can vary significantly. Some individuals notice clear pre-attack warning signs, while others have little to no premonition.

Early Warning Signs
Some individuals report experiencing warning signs before a vertigo attack. These can include increased aural fullness in the affected ear, louder tinnitus, muffled hearing, mild dizziness, or a sense that their balance is "off." These warning signs are not universal but, when present, can prompt individuals to move to a safer location, avoid driving, sit or lie down, and inform others of their condition.
During a Vertigo Attack
During a vertigo attack, the sensation can be intense, with the feeling of the room spinning or moving even when stationary. Attacks typically last from 20 minutes to several hours and may be accompanied by nausea, vomiting, sweating, or difficulty walking. The recommended response is usually to sit or lie down, avoid sudden head movements, and wait for the spinning sensation to subside. Any new, severe, frequent, or hearing-associated vertigo attacks warrant prompt medical evaluation.
Between Episodes and Remission
Following an attack, some individuals feel almost normal. Others may experience lingering fatigue, imbalance, or a sense that their balance has not fully recovered, alongside persistent tinnitus or hearing difficulties. Hearing can fluctuate significantly, particularly in the earlier stages, while symptoms may become more persistent in some individuals over time. Periods of remission are common and can last for months or even years. Symptom diaries remain valuable tools for tracking the frequency, duration, and severity of attacks, aiding in diagnosis and treatment planning.
The Underlying Cause: Endolymphatic Hydrops
The fluctuating nature of Meniere’s disease symptoms is linked to abnormal changes in fluid pressure within the inner ear, a condition known as endolymphatic hydrops. The inner ear houses delicate structures responsible for converting sound into hearing signals and movement into balance signals.
Imagine the inner ear as a sensitive instrument. When fluid pressure fluctuates, the signals for hearing and balance can become distorted. Initially, this might result in intermittent symptoms. Over time, repeated disruption can damage the delicate hair cells and other inner ear structures crucial for hearing and balance, leading to more permanent changes. This explains the shift from fluctuating hearing loss and vertigo attacks to more permanent hearing loss, tinnitus, and imbalance.

Diagnosing Meniere’s Disease
Diagnosing Meniere’s disease is typically performed by an ENT (Ear, Nose, and Throat) specialist. There isn’t a single definitive test; diagnosis relies on a combination of factors, including a thorough review of symptoms, medical history, hearing tests, and the exclusion of other potential causes. Key diagnostic indicators often include:
- Recurring vertigo attacks: Characterized by a spinning sensation, lasting from 20 minutes to 12 hours.
- Fluctuating hearing loss: Documented through audiometric testing, often showing low-frequency hearing loss during or after attacks.
- Tinnitus: A ringing, roaring, or buzzing sound in the affected ear.
- Aural fullness: A sensation of pressure or blockage in the ear.
- Absence of other identifiable causes: Ruling out other neurological or vestibular disorders.
Given that other conditions can mimic these symptoms, specialists will conduct thorough evaluations to differentiate Meniere’s disease from other possibilities such as migraine-associated vertigo, vestibular neuritis, ear infections, neurological conditions, or other inner ear disorders.
Treatment Options and Long-Term Management
Currently, there is no cure for Meniere’s disease, but treatment strategies focus on managing symptoms, mitigating safety risks, and enhancing the overall quality of life. Treatment plans are individualized, taking into account the patient’s specific symptoms, hearing levels, balance function, overall health, and the stage of the disease.
Lifestyle and Safety Adjustments
Some individuals benefit from dietary modifications (e.g., reduced salt intake), stress management techniques, identifying and avoiding personal triggers, and implementing safety measures at home and work to prevent falls.
Medication for Vertigo or Nausea
Medications can be prescribed to alleviate vertigo attacks, nausea, and vomiting. The choice of medication depends on individual medical history and should be determined in consultation with a healthcare professional.

Vestibular Rehabilitation
For chronic imbalance, vestibular rehabilitation therapy (VRT) may be recommended. VRT is a specialized form of physical therapy designed to help the brain compensate for inner ear deficits and reduce long-term balance problems, rather than stopping an acute vertigo attack.
Hearing Support
When hearing loss significantly impacts daily communication, an ENT specialist or audiologist may discuss further options. These can range from conventional hearing aids and CROS systems to bone conduction solutions. In cases of severe, permanent hearing loss, a cochlear implant may be considered, depending on the individual’s hearing test results and medical history.
Hearing Support in Later Stages: Real-Life Impact
The impact of Meniere’s disease on hearing can be profound. For instance, Helen, an audiologist from Australia, experienced single-sided deafness due to Meniere’s disease. After receiving a MED-EL cochlear implant, she reported a significant reduction in her tinnitus: "My MED-EL cochlear implant also silenced my tinnitus, which is really quite amazing and a huge relief." This real-life experience underscores the potential benefits of advanced hearing solutions in managing the long-term consequences of Meniere’s disease, particularly severe hearing loss and associated tinnitus. Improved access to sound can also bolster confidence in social situations and enhance personal independence.
Long-Term Outlook and When to Seek Medical Help
The long-term outlook for Meniere’s disease is variable. Some individuals experience infrequent attacks with extended symptom-free periods, while others develop more persistent hearing and balance difficulties. Symptoms may stabilize over time but typically do not disappear entirely. While most cases affect only one ear, in some instances, the condition can eventually affect both ears.
It is imperative to seek medical advice if experiencing:

- Recurring vertigo attacks.
- Fluctuating or progressive hearing loss.
- Persistent tinnitus or aural fullness.
- Sudden, severe dizziness or disorientation.
New or severe dizziness, especially when accompanied by symptoms such as weakness, speech difficulty, chest pain, severe headaches, or other urgent warning signs, requires immediate medical assessment.
Key Takeaway: A Framework for Understanding
The commonly discussed four stages of Meniere’s disease offer a valuable framework for understanding how symptoms may progress over time. However, they should be interpreted as general descriptions of possible symptom patterns rather than a definitive, fixed pathway. Each individual’s experience with Meniere’s disease is unique. The stages of Meniere’s disease should not be used for self-diagnosis. With appropriate medical support, many individuals can effectively manage their symptoms, reduce safety risks, and access suitable hearing support when long-term hearing loss impacts their daily lives.
If you are experiencing symptoms such as vertigo, tinnitus, ear fullness, or changes in hearing, it is crucial to consult with an ENT specialist or a hearing care professional to understand your condition and explore the most appropriate next steps for your care.



